Infection Control Audit Checklist Template

Most infection control failures are not a missing policy. They are a handrub dispenser that ran empty, a sharps bin past its fill line or a commode nobody cleaned between patients, and an audit that found them last quarter with no owner for the fix.

Last reviewed: October 2026

Standard infection control precautions only protect patients if they are followed on every shift, and an audit is how a team finds out whether they are. This free infection control audit checklist is for IPC teams, link practitioners, ward and practice managers and care home managers who audit one area at a time. One run is one audit of one ward, clinic, GP or dental practice, or care home area. It plans the audit from last time’s open actions, then works through the ten elements of standard precautions in NHS England’s National IPC Manual on the day of the visit: the environment, hand hygiene and PPE, sharps, linen and waste, care equipment, patient placement and respiratory hygiene, and staff safety and training. It ends with scores, an action plan, the IPC lead’s sign-off and feedback to the team. A first question shows England or United States references, and a re-audit phase appears when a score falls below your pass mark.

An Infection Control Audit Checks Practice Where Care Happens

NHS England’s National Infection Prevention and Control Manual (NIPCM) says standard infection control precautions are to be used by all staff, in all care settings, at all times, for all patients, whether infection is known to be present or not. It also says monitoring of those precautions must be ongoing. An infection control audit is that monitoring for one area: an auditor walks the ward, clinic, practice or care home, watches care as it happens, checks the records and scores what they find against the ten elements of standard precautions. In England the Code of Practice under the Health and Social Care Act 2008 asks registered providers to monitor their IPC policies with a rolling programme of audit. In the United States, CDC’s core practices call it performance monitoring and feedback.

The audit is not the only infection control check a service runs. Instrument reprocessing has its own record for every load, kept with the Medical Equipment Sterilization Checklist. Preparing evidence for a regulator is a separate job again, covered by the CQC Inspection Readiness Checklist and the Joint Commission Survey Readiness Checklist. Your IPC audits are some of the evidence those two checklists gather.

IPC audit

Checks everyday practice in one area

Asks: are the standard precautions in place and followed today, by the people on shift?

When: on the cycle your organisation sets, and again after a poor result.

Output: a score for each element, findings, an action plan with owners and the IPC lead’s sign-off.

Reprocessing record

Shows each instrument load was reprocessed

Asks: was every step of cleaning, inspection, packaging, sterilisation and storage done for this load?

When: every load, in the decontamination or sterile services area.

Output: a load record that traces each tray to its cycle.

Inspection readiness

Prepares the evidence for the regulator

Asks: can we show the regulator that our systems work, including how we manage infection risk?

When: continuously, ahead of an inspection or survey.

Output: evidence organised by the regulator’s questions or standards, with your audits among it.

What the Infection Control Audit Checklist Covers

Eight phases take one audit from planning to sign-off. Phases 2 to 6 follow the ten elements of standard infection control precautions on the day of the visit. Phase 8 appears only when a score falls below the pass mark your organisation sets.

  1. Phase 1

    Phase 1: Plan the Audit

    5 tasks

    Agree what the audit covers and read the records before the visit. An audit that does not start from last time’s open actions tends to find the same problems again.

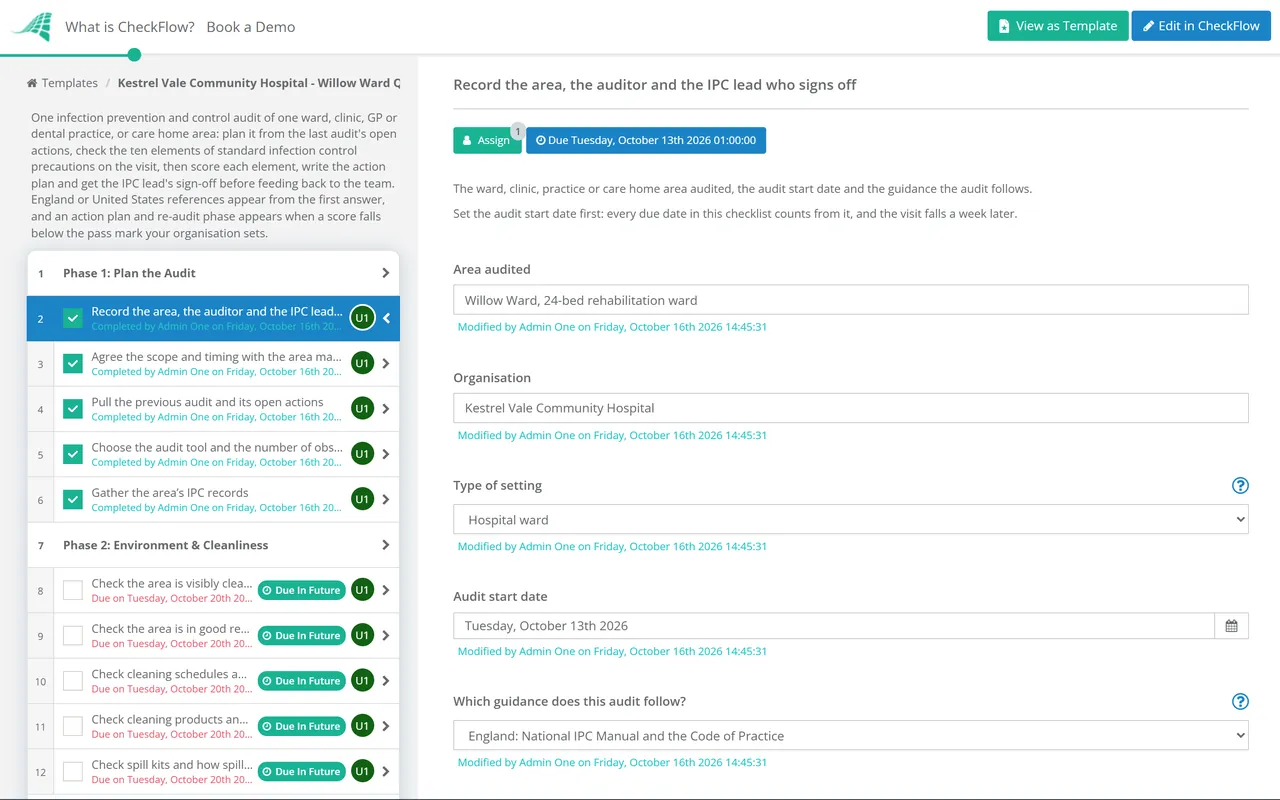
    • Record the area, the auditor and the IPC lead who signs off — the ward, clinic, practice or care home area audited, the audit start date and the guidance the audit follows
    • Agree the scope and timing with the area manager — which of the ten standard infection control precautions apply here, the visit date, and the times when care can be watched
    • Pull the previous audit and its open actions — which actions were closed, which slipped, and which elements scored lowest last time
    • Choose the audit tool and the number of observations — the NHS England SICPs monitoring tool or your local tool, and how many hand hygiene, PPE and equipment observations your policy asks for
    • Gather the area’s IPC records — cleaning schedules, equipment decontamination and maintenance records, sharps injury reports and any outbreak or surveillance data since the last audit
  2. Phase 2

    Phase 2: Environment & Cleanliness

    5 tasks

    The NIPCM says the care environment must be visibly clean, free from non-essential items and equipment, well maintained and in a good state of repair.

    • Check the area is visibly clean and free from clutter — curtains, bathrooms, floors, high areas and high-touch surfaces such as door handles, bed rails and light switches, with nothing stored on the floor
    • Check the area is in good repair — damaged floors, walls, furniture and fittings reported to estates, and ventilation and water safety checks in date
    • Check cleaning schedules and responsibilities — who cleans what, how often and how, whether staff on shift know their part, and how to ask for extra cleaning
    • Check cleaning products and technique — the locally approved product for each surface, cloths and solutions changed between tasks, and staff who can describe what they use and why
    • Check spill kits and how spills are managed — a spill kit in the area, staff who know where it is, and the right product and technique for blood and body fluid spills
  3. Phase 3

    Phase 3: Hand Hygiene & PPE

    8 tasks

    Most of this phase is watching care as it happens. Record what you saw, not what staff say they usually do, and ask about anything you could not judge by watching.

    • Check clinical hand wash basins and dispensers — basins used only for hand hygiene, clean and in good repair, with wall-mounted liquid soap and paper towels and a technique poster beside them
    • Check alcohol-based handrub at the point of care — wall-mounted or personal dispensers as near to the point of care as possible, filled and working
    • Check staff are bare below the elbow — forearms exposed, no hand or wrist jewellery beyond one plain ring, short clean nails with no artificial nails or nail products, and cuts covered with a waterproof dressing
    • Observe hand hygiene at the five moments — before touching a patient, before clean or aseptic procedures, after body fluid exposure risk, after touching a patient and after touching their surroundings
    • Observe hand washing and handrub technique — the right choice of soap and water or handrub, every surface of the hands covered, enough time taken, and hands dried with paper towels
    • Check PPE stock, storage and location — enough of each item close to the point of use, stored clean and dry, and within its expiry date
    • Observe PPE chosen and changed for each task — gloves and aprons worn when exposure to blood or body fluids is anticipated, changed between tasks and patients, with hand hygiene after removal
    • Check PPE removal and disposal — clear space to put PPE on and take it off, a bin at the point of removal, the right waste stream, and reusable eye protection decontaminated after each use
  4. Phase 4

    Phase 4: Sharps, Linen & Waste

    6 tasks

    Containers, bags and stores are quick to check and easy to get wrong. The NIPCM’s rules here are specific, so check them one by one.

    • Check sharps containers — assembled correctly, labelled with the point of origin and the dates of assembly and disposal, temporary closure used, and not filled beyond the fill line
    • Observe how sharps are used and discarded — no re-sheathing or passing hand to hand, discarded at the point of use by the person who used them, needle and syringe as one unit, and safety mechanisms deployed first
    • Check clean linen storage — off the floor in a clean, dry, designated cupboard or a covered trolley, out of plastic bags and kept apart from used linen
    • Check used and infectious linen handling — not shaken, sorted or put on the floor, bagged at the point of care, bags no more than two-thirds full, and infectious linen in a water-soluble bag, tagged and dated
    • Check waste is segregated at the point of use — each item into the right colour-coded bag, box or sharps container, straight away and as close to where it was used as possible
    • Check waste bags, labels and the waste store — bags no more than two-thirds full and tied with a swan neck, labelled back to the area, and held in a lockable store with no build-up
  5. Phase 5

    Phase 5: Equipment, Placement & Respiratory Hygiene

    7 tasks

    Communal equipment moves between patients, and an infection can move with it. Placement and isolation decisions are checked against the patient notes, not against memory.

    • Check sterile items before use — packaging intact with no sign of contamination, expiry date valid, and any sterility indicator showing the process was completed
    • Inspect the area’s reusable care equipment — items such as commodes, hoists, trolleys and monitors: clean, free from dust, blood and body fluids, and in good repair
    • Check equipment decontamination protocols and records — who decontaminates what, how often and with which product, planned preventative maintenance for medical devices, and staff who can describe the product for blood-contaminated equipment
    • Check single-use items are not reused — items with the single-use symbol discarded after one use, needles and syringes used once, and no single-dose vial or IV bag shared between patients
    • Check patients were assessed for infection risk on arrival — assessed on arrival and reviewed during their stay, recorded in the notes, and their infection status passed on when they move to another service
    • Check isolation and cohorting decisions — patients who need it isolated or cohorted while awaiting results, signs in place, and dedicated equipment or a decontamination plan for isolation rooms
    • Check respiratory and cough hygiene — tissues, a bag or bin for used tissues and hand hygiene for patients with symptoms, help for those who need it, and signs at the entrance asking people with respiratory symptoms to tell reception
  6. Phase 6

    Phase 6: Staff Safety & Training

    5 tasks

    The NIPCM says staff must understand what to do after a significant occupational exposure, and that there is a legal requirement to report all sharps injuries and near misses to line managers or employers.

    • Ask staff what a significant occupational exposure is — a skin-breaking injury from a needle, instrument, bone fragment or bite, or blood or another high-risk body fluid on broken skin, the eyes or the mouth
    • Check staff know the first aid and reporting steps — let a wound bleed without squeezing, wash it with warm running water and soap, irrigate eyes or mouth with water, report it, and get occupational health or A&E advice
    • Review sharps injuries and exposures since the last audit — each one reported, investigated and followed up, with the cause dealt with
    • Confirm occupational health and immunisation arrangements — staff can reach occupational health, immunisation records are kept, and staff with an infection that could spread know not to work
    • Check IPC training records for every staff group — induction and refresher training in date, including bank and agency staff, volunteers and contractors, and competence signed off for aseptic technique
  7. Phase 7

    Phase 7: Score, Findings & Sign-off

    8 tasks

    Score the result the same way every time, so this audit can be compared with the last one. The IPC lead signs off the report before it goes to the team, and nothing after the sign-off can be completed until they do.

    • Escalate findings that need immediate action — tell the person in charge before you leave, and record what was done on the day
    • Score each element — the share of applicable checks that were compliant, element by element and overall, leaving out checks not observed or not applicable
    • Compare the scores with your pass mark — the pass mark your organisation set on the first task; any element below it switches on Phase 8
    • Record good practice and areas for improvement — for each element, what was done well, what needs to improve and what needs immediate action, in the words of the audit report
    • Write the action plan with owners and deadlines — one action per finding, with who will do it and by when, the most serious first
    • IPC lead signs off the audit report — the scores, findings and action plan, before they are shared, with the decision and any conditions recorded
    • Feed back the results to the area team — what went well, what must change and who owns each action, at a team meeting or huddle, and to the area manager in writing
    • Report the results and set the next audit date — to your IPC committee or governance meeting, and into the annual IPC statement where one is kept, with open actions carried into the next audit
  8. Phase 8 — If Needed

    Phase 8: Action Plan & Re-audit

    5 tasks

    Shown only when a score falls below the pass mark your organisation sets. The actions are worked through, then the elements that fell short are audited again.

    • Give targeted training where practice fell short — a short session, a demonstration or a one-to-one on the element concerned, recorded for each member of staff
    • Track each action to its deadline — follow up each owner before the date, and escalate any action that slips to the IPC lead
    • Re-audit the elements below the pass mark — with the same tool and the same scoring, on the date the IPC lead agreed, and by a different auditor where you can
    • Feed back the re-audit result to the team — the new scores, what changed and anything still to do
    • IPC lead closes the action plan — or sets a further re-audit date if an element is still below the pass mark

The Ten Standard Infection Control Precautions: What to Check

The NIPCM sets out ten elements of standard infection control precautions (SICPs). NHS England’s SICPs monitoring tool has a sheet for each one, and this checklist covers all ten across Phases 2 to 6. Use the right-hand column as a starting point for each element, then add what your own policy asks for.

SICP element What the NIPCM says What to check on the audit
1. Patient placement and assessment of infection riskPatients are assessed for infection risk on arrival at the care area and reviewed throughout their stay, and the assessment guides where they are placed.Assessments recorded in the notes, isolation or cohorting while results are awaited, and infection status passed on at transfer.
2. Hand hygieneHandrub at the point of care for routine hand hygiene; soap and water when hands are visibly soiled and for vomiting, diarrhoea or a gastrointestinal infection.Basins and dispensers, bare below the elbow, the five moments and technique, watched in practice.
3. Respiratory and cough hygieneCover the nose and mouth with a tissue, dispose of it promptly and clean hands afterwards. Staff help patients who need assistance.Tissues, a bag or bin and hand hygiene for patients with symptoms, and signs at the entrance.
4. Personal protective equipmentPPE is chosen by assessing the likely exposure to blood and body fluids, stored close to the point of use, single use unless the manufacturer says otherwise, and changed after each patient or task.Stock and storage, the right PPE for each task, no gloves for tasks without exposure, and safe removal.
5. Safe management of care equipmentReusable non-invasive equipment is decontaminated between each use, after contamination, at set intervals and before servicing or repair. Single-use items are never reused.Ten items of equipment inspected, decontamination protocols and planned maintenance records.
6. Safe management of the care environmentThe environment is visibly clean, free from non-essential items, well maintained and adequately ventilated, and routinely cleaned to the National Cleaning Standards.Curtains, bathrooms, floors, high areas and high-touch surfaces, cleaning schedules and products.
7. Safe management of linenClean linen is stored off the floor and apart from used linen. Used linen is not shaken or sorted, and infectious linen goes in a water-soluble bag.Clean linen storage, bags at the point of care, two-thirds full at most, tagged and dated.
8. Safe management of blood and body fluid spillagesAll spillages are treated as hazardous and dealt with immediately by trained staff, with clear responsibility in each area.A spill kit in the area, and staff who know the product and technique.
9. Safe disposal of waste, including sharpsWaste goes into the right colour-coded stream at the point of use. Sharps containers are labelled, dated, closed when not in use and not filled beyond the fill line.Segregation, bag filling and labels, the lockable store, and every sharps container in the area.
10. Occupational safety: prevention of exposureSharps are not re-sheathed or passed hand to hand, and are discarded by the user at the point of use. Staff know what a significant exposure is and what to do.Sharps practice watched, staff asked about exposures, and injuries since the last audit reviewed.

Scoring and the pass mark. Neither the NIPCM nor the Code of Practice sets a national pass mark for an IPC audit. The NHS England monitoring tool asks the auditor to mark areas of good practice, areas requiring improvement and areas requiring immediate action, and says each organisation should decide locally how often to monitor. Set your own pass mark on the first task, leave checks you could not observe out of the score, and score every audit the same way.

Outside England. CDC’s core infection prevention and control practices group the same precautions under standard precautions: hand hygiene, environmental cleaning and disinfection, injection and medication safety, risk assessment with PPE, minimising potential exposures and reprocessing reusable equipment. Choose United States on the first task to show CDC’s wording on the tasks that need it. Elsewhere in the UK, choose the third option and work to your own nation’s guidance: the NIPCM notes that some operational details differ across the nations.

Why Run Infection Control Audits in CheckFlow?

1

Every area audited on its cycle

A recurring schedule starts each area’s audit on the cycle you choose, quarterly for example, assigned to its auditor. The due dates count from the audit start date, so planning, the visit, the report and the sign-off land in order, and a score below your pass mark adds the re-audit phase to that run.

2

No report goes out unsigned

The IPC lead is chosen on the first task. The sign-off is assigned to them alone, and nothing after the approval step can be completed until they record a decision. Their decision, any conditions and the report itself stay on the checklist with the date.

3

Scores you can compare

Every run keeps its scores table, photos and action plan with names and dates. The Reports Grid lists every area’s audit with the answers given, including the overall score, and Analytics shows overdue and late tasks by person and step.

CheckFlow does not decide whether practice in an area is safe. That judgement is the auditor’s and the IPC lead’s, recorded on each task. It runs the audit around it: who does what, by when, with what evidence, and who signed it off. CheckFlow’s healthcare checklist software shows how the same approach handles other clinical processes.

An infection found on the ward may also be an incident: the Healthcare Incident Reporting Process Checklist takes it through investigation. Audit results feed the CQC Inspection Readiness Checklist and the Joint Commission Survey Readiness Checklist, instrument loads are recorded with the Medical Equipment Sterilization Checklist, and new staff get their IPC induction through the New Nurse Onboarding Checklist.

AI generator

Didn’t find what you need? Describe it.

Describe the process in a sentence and the AI checklist generator drafts the phases and tasks for you.

Frequently Asked Questions

What is an infection control audit?

An infection control audit is a structured check of infection prevention and control practice in one area, such as a ward, clinic, GP or dental practice, or care home. The auditor watches care as it happens, inspects the environment and equipment, checks the records and scores what they find, usually against the ten elements of standard infection control precautions. The result is a score for each element, a list of findings, an action plan with owners and deadlines, and a sign-off by the IPC lead. The Code of Practice describes audit as part of a quality improvement process.

What should an infection control audit checklist include?

In England, the ten elements of standard infection control precautions from the National IPC Manual: patient placement and assessment of infection risk, hand hygiene, respiratory and cough hygiene, personal protective equipment, safe management of care equipment, the care environment, linen, blood and body fluid spillages, safe disposal of waste including sharps, and occupational safety. A useful audit also reviews last time’s open actions, staff training records and sharps injuries, then ends with scores, an action plan, the IPC lead’s sign-off and feedback to the team.

How often should infection control audits be done?

There is no single national frequency. NHS England’s SICPs monitoring tool says each organisation should decide locally how often to monitor, and suggests completing it first to set a baseline. The Code of Practice asks registered providers to monitor their IPC policies with a rolling programme of audit. You may want to audit higher-risk areas more often, and to repeat an audit sooner after a poor result or an outbreak. Set the cycle in your IPC programme and run it as a recurring schedule so no area is missed.

What is a pass mark for an infection control audit?

National guidance does not set one. The NIPCM and the Code of Practice say what good practice looks like, not what percentage counts as a pass. The NHS England monitoring tool asks the auditor to mark areas of good practice, areas requiring improvement and areas requiring immediate action. Agree a pass mark, or a red, amber and green scale, in your own IPC policy. Record it on the first task of this checklist, and score every audit the same way so results can be compared over time.

Is the NHS England SICPs monitoring tool mandatory?

No. NHS England says the monitoring tool is not compulsory. It can be used in place of, or in addition to, the local tools organisations already use to check that the guidance in the National IPC Manual is followed. The tool has a sheet for each of the ten elements and a summary sheet, with space for five hand hygiene observations, five PPE observations and ten items of reusable equipment. It says local policy decides how many observations to make in a period. This checklist follows the same ten elements.

Does the Code of Practice apply to care homes, GP and dental practices?

Yes. The Health and Social Care Act 2008 Code of Practice applies to all registered providers of health and adult social care in England, including care homes, primary medical care and primary dental care. CQC applies it in proportion to the setting, so a care home is not expected to have the same facilities as an acute hospital. The code has appendices for adult social care, dental and primary medical care, and each names audits undertaken and the actions that followed as part of the annual IPC statement.

Who should carry out an infection control audit?

Someone trained to audit, using a standard tool. The Code of Practice gives responsibility for IPC to the Director of IPC in NHS organisations and to a designated IPC lead elsewhere, who in a care home, GP or dental practice could be the registered provider, the registered manager or another member of staff. CDC’s core practices say the staff who monitor practice should be trained and use standardised tools and definitions. An auditor from outside the area often sees what has become normal there. The IPC lead signs off the result.

Is CheckFlow free for this template?

14-day free trial, no card required. The Business plan is $10 per user per month after the trial. Full details at checkflow.io/pricing.

Audit Every Area, Then Close Every Action

Free trial — no credit card required.

14-day free trial, no credit cardFull refund in your first 30 daysUS or EU hosting